Showing posts with label cautionary tale. Show all posts

Tuesday, January 29, 2019

Obesity, undernutrition and climate change link


https://uk.yahoo.com/news/three-global-pandemics-threaten-humanity-theyre-linked-food-111222156.html

Three global pandemics threaten humanity (and they’re all linked to our food)

 Rob Waugh,Yahoo News UK il y a 5 heures 

Humanity is under threat from three global pandemics, and they’re all linked to the way we eat, a new report has argued.
‘Big Food’ companies are driving global epidemics in obesity, undernutrition and climate change, and all of them threaten human beings.
A new report by the Lancet Commission on objesity recruited 26 experts from 14 countries.
The researchers found that ‘Big Food’ companies are driven purely by profit and economic growth, and are promoting a ‘syndemic’, with people stricken by obesity, undernutrition and farms driving greenhouse gas emissions.

Professor Boyd Swinburn of the University of Auckland says, ‘Until now, undernutrition and obesity have been seen as polar opposites of either too few or too many calories.
The growing influence of ‘big food’ needs to be curbed globally if the problems of obesity, malnutrition and climate change are to be tackled in time, a global report said.
‘In reality, they are both driven by the same unhealthy, inequitable food systems, underpinned by the same political economy that is single-focused on economic growth, and ignores the negative health and equity outcomes.
‘Climate change has the same story of profits and power ignoring the environmental damage caused by current food systems, transportation, urban design and land use. Joining the three pandemics together as The Global Syndemic allows us to consider common drivers and shared solutions, with the aim of breaking decades of policy inertia.’

Tuesday, January 01, 2019

'the dangers of false certainty'


https://edition.cnn.com/2018/12/21/health/medical-uncertainty-diagnosis-afm/index.html

'Widespread and dangerous': Facing medical uncertainty, some doctors tell patients it's all in their heads


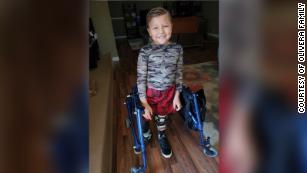
(CNN)When 7-year-old Bailey Sheehan arrived at a hospital in Oregon partially paralyzed, a doctor said the girl was faking her symptoms to get her parents' attention because she was jealous of her new baby sister.
But that doctor was proved wrong when an MRI showed that the girl had acute flaccid myelitis or AFM, a polio-like disease that's struck hundreds of children since 2014.
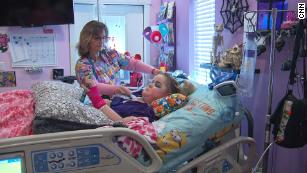
Erin Olivera, mother of a child with AFM and founder of a private Facebook page for parents of 400 children with the disease, says Bailey's experience is hardly unique. She estimates that based on postings by parents, as many as 1 in 10 children were told that the paralysis was all in their heads when they first sought medical care.
    Experts who study the art and science of diagnosis say the problem goes beyond this one rare disease. They say that in general, when presented with a puzzling disease, physicians too often leap to a diagnosis of a psychiatric problem.
    "Mental disorders become the default position to deal with medical uncertainty," said Dr. Allen Frances, former chair of psychiatry at the Duke University School of Medicine. "It's widespread, and it's dangerous."
    Dr. Mark Graber, president emeritus of the Society to Improve Diagnosis in Medicine, added, "It's a tendency that physicians have when they can't find a physical cause.
    "It's bad. It's very bad."

    Bailey's story

    Bailey was a healthy little girl until October 28, 2014, when she suddenly couldn't move her neck or her right shoulder or leg.
    A rehabilitation expert at a children's hospital said Bailey wasn't really paralyzed, according to her mother, Mikell Sheehan.
    The doctor said the paralysis was an emotional reaction to her sister's birth four months earlier. He diagnosed Bailey with a mental condition called conversion disorder.
    Sheehan told the doctor off.
    Bailey Sheehan was diagnosed with AFM after her mother disagreed with an initial diagnosis.
    "I said, 'You've been with my child for 15 minutes, and you think it's psychological? Get out of my face,' " she remembered.
    Sheehan said the doctor hinted that she was unstable.
    "He said, you know, 'moms with new babies don't get enough sleep,' " she said.
    Bailey's regular pediatrician, who'd known the girl since birth, disagreed with the diagnosis and pushed for further testing. That's when the MRI showed that she had AFM.
    Armed with the correct diagnosis, Bailey received treatment for AFM, including extensive physical therapy, and four years later is walking again.
    "We were lucky that her pediatrician was such an advocate for us, but I don't know if everyone's that lucky," Sheehan said.
    Sheehan says she understands why doctors didn't immediately think of AFM for her daughter, because the disease was not well-known four years ago. But there are several other causes of paralysis in children, and she wonders why her daughter didn't get a full round of testing for those.
    Dr. Benjamin Greenberg, a neurologist who's seen cases of AFM across the country, said that even this year, when AFM has made headlines nationally, parents have told him that doctors have missed the disease and suggested that their children were faking their paralysis.
    "The stories I can tell are maddening and saddening," said Greenberg, associate professor of neurology at UT Southwestern Medical Center.
    Four years later, Sheehan says, she still feels the scars from her daughter's misdiagnosis.
    "You feel violated and wrongly accused," she said.

    The dangers of false certainty

    Though there's no data indicating how frequently doctors misdiagnose physical conditions as psychiatric ones, experts in the field of diagnosis say they see it all too often.
    It typically starts when a patient has a perplexing illness and doctors feel a need to come up with a diagnosis.
    "Doctors are uncomfortable with not having answers," Frances said.
    The consequences can be "catastrophic," he said, because a misdiagnosis can lead to a patient receiving treatment for a disease they don't have and missing out on treatment for the disease they do have.
    "False certainty is much more dangerous than uncertainty," he said.
    The American Medical Association and the American College of Emergency Physicians declined requests for comment.

    Graber, who is also professor emeritus of medicine at the Stony Brook University in New York, said part of the problem is that medical students are taught that physical symptoms sometimes have a psychological basis. That's true, he said, but doctors need to thoroughly test for physical problems before defaulting to a psychiatric diagnosis.
    "Physicians have an obligation to do a thorough workup before turning to a psychological explanation," he said. "When a doctor can't find a cause, that's a great time to get a second opinion or consult with a specialist."
      Frances added that it's OK for a doctor to simply say "I don't know."
      "Doctors need to learn to embrace medical uncertainty," he said.

      Saturday, December 22, 2018

      When 'average' isn't representative

      https://www.thestar.com/news/insight/2016/01/16/when-us-air-force-discovered-the-flaw-of-averages.html


      When U.S. air force discovered the flaw of averages

      In the late 1940s, the United States air force had a serious problem: its pilots could not keep control of their planes. Although this was the dawn of jet-powered aviation and the planes were faster and more complicated to fly, the problems were so frequent and involved so many different aircraft that the air force had an alarming, life-or-death mystery on its hands. “It was a difficult time to be flying,” one retired airman told me. “You never knew if you were going to end up in the dirt.” At its worst point, 17 pilots crashed in a single day.
      The two government designations for these noncombat mishaps were incidents and accidents, and they ranged from unintended dives and bungled landings to aircraft-obliterating fatalities. At first, the military brass pinned the blame on the men in the cockpits, citing “pilot error” as the most common reason in crash reports. This judgment certainly seemed reasonable, since the planes themselves seldom malfunctioned. Engineers confirmed this time and again, testing the mechanics and electronics of the planes and finding no defects. Pilots, too, were baffled. The only thing they knew for sure was that their piloting skills were not the cause of the problem. If it wasn’t human or mechanical error, what was it?
      In the early 1950s, the U.S. air force measured more than 4,000 pilots on 140 dimensions of size, in order to tailor cockpit design to the "average" pilot. But it turned out the average airman didn't exist.
      In the early 1950s, the U.S. air force measured more than 4,000 pilots on 140 dimensions of size, in order to tailor cockpit design to the "average" pilot. But it turned out the average airman didn't exist.  (U.S. NATIONAL ARCHIVES /THE ASSOCIATED PRESS FILE PHOTO)
      After multiple inquiries ended with no answers, officials turned their attention to the design of the cockpit itself. Back in 1926, when the army was designing its first-ever cockpit, engineers had measured the physical dimensions of hundreds of male pilots (the possibility of female pilots was never a serious consideration), and used this data to standardize the dimensions of the cockpit. For the next three decades, the size and shape of the seat, the distance to the pedals and stick, the height of the windshield, even the shape of the flight helmets were all built to conform to the average dimensions of a 1926 pilot.
      Now military engineers began to wonder if the pilots had gotten bigger since 1926. To obtain an updated assessment of pilot dimensions, the air force authorized the largest study of pilots that had ever been undertaken. In 1950, researchers at Wright Air Force Base in Ohio measured more than 4,000 pilots on 140 dimensions of size, including thumb length, crotch height, and the distance from a pilot’s eye to his ear, and then calculated the average for each of these dimensions. Everyone believed this improved calculation of the average pilot would lead to a better-fitting cockpit and reduce the number of crashes — or almost everyone. One newly hired 23-year-old scientist had doubts.
      Lt. Gilbert S. Daniels was not the kind of person you would normally associate with the testosterone-drenched culture of aerial combat. He was slender and wore glasses. He liked flowers and landscaping and in high school was president of the Botanical Garden Club. When he joined the Aero Medical Laboratory at Wright Air Force Base straight out of college, he had never even been in a plane before. But it didn’t matter. As a junior researcher, his job was to measure pilots’ limbs with a tape measure.
      It was not the first time Daniels had measured the human body. The Aero Medical Laboratory hired Daniels because he had majored in physical anthropology, a field that specialized in the anatomy of humans, as an undergraduate at Harvard. During the first half of the 20th century, this field focused heavily on trying to classify the personalities of groups of people according to their average body shapes — a practice known as “typing.” For example, many physical anthropologists believed a short and heavy body was indicative of a merry and fun-loving personality, while receding hairlines and fleshy lips reflected a “criminal type.”
      Daniels was not interested in typing, however. Instead, his undergraduate thesis consisted of a rather plodding comparison of the shape of 250 male Harvard students’ hands. The students Daniels examined were from very similar ethnic and socio-cultural backgrounds (namely, white and wealthy), but, unexpectedly, their hands were not similar at all. Even more surprising, when Daniels averaged all his data, the average hand did not resemble any individual’s measurements. There was no such thing as an average hand size. “When I left Harvard, it was clear to me that if you wanted to design something for an individual human being, the average was completely useless,” Daniels told me.
      So when the air force put him to work measuring pilots, Daniels harboured a private conviction about averages that rejected almost a century of military design philosophy. As he sat in the Aero Medical Laboratory measuring hands, legs, waists and foreheads, he kept asking himself the same question in his head: How many pilots really were average?
      He decided to find out. Using the size data he had gathered from 4,063 pilots, Daniels calculated the average of the 10 physical dimensions believed to be most relevant for design, including height, chest circumference and sleeve length. These formed the dimensions of the “average pilot,” which Daniels generously defined as someone whose measurements were within the middle 30 per cent of the range of values for each dimension. So, for example, even though the precise average height from the data was five foot nine, he defined the height of the “average pilot” as ranging from five-seven to five-11. Next, Daniels compared each individual pilot, one by one, to the average pilot.
      Before he crunched his numbers, the consensus among his fellow air force researchers was that the vast majority of pilots would be within the average range on most dimensions. After all, these pilots had already been pre-selected because they appeared to be average sized. (If you were, say, six foot seven, you would never have been recruited in the first place.) The scientists also expected that a sizable number of pilots would be within the average range on all 10 dimensions. But even Daniels was stunned when he tabulated the actual number.
      Zero.
      Out of 4,063 pilots, not a single airman fit within the average range on all 10 dimensions. One pilot might have a longer-than-average arm length, but a shorter-than-average leg length. Another pilot might have a big chest but small hips. Even more astonishing, Daniels discovered that if you picked out just three of the ten dimensions of size — say, neck circumference, thigh circumference and wrist circumference — less than 3.5 per cent of pilots would be average sized on all three dimensions. Daniels’s findings were clear and incontrovertible. There was no such thing as an average pilot. If you’ve designed a cockpit to fit the average pilot, you’ve actually designed it to fit no one.
      Daniels’ revelation was the kind of big idea that could have ended one era of basic assumptions about individuality and launched a new one. But even the biggest of ideas requires the correct interpretation. We like to believe that facts speak for themselves, but they most assuredly do not. After all, Gilbert Daniels was not the first person to discover there was no such thing as an average person.

      Norma was designed to represent the "ideal" female form, based on measurements collected from 15,000 young adult women. The statue on display at the Cleveland Health Museum was the creation of a gynecologist, Dr. Robert L. Dickinson, and his collaborator Abram Belskie.
      A misguided ideal
      Seven years earlier, the Cleveland Plain Dealer announced on its front page a contest co-sponsored with the Cleveland Health Museum and in association with the Academy of Medicine of Cleveland, the School of Medicine and the Cleveland Board of Education. Winners of the contest would get $100, $50, and $25 war bonds, and 10 additional lucky women would get $10 worth of war stamps. The contest? To submit body dimensions that most closely matched the typical woman, “Norma,” as represented by a statue on display at the Cleveland Health Museum.
      Norma was the creation of a well-known gynecologist, Dr. Robert L. Dickinson, and his collaborator Abram Belskie, who sculpted the figure based on size data collected from 15,000 young adult women. Dr. Dickinson was an influential figure in his day: chief of obstetrics and gynecology at the Brooklyn Hospital, president of the American Gynecological Society and chairman of obstetrics at the American Medical Association. He was also an artist — the “Rodin of obstetrics,” as one colleague put it — and throughout his career he used his talents to draw sketches of women, their various sizes and shapes, to study correlations of body types and behaviour.
      Like many scientists of his day, Dickinson believed the truth of something could be determined by collecting and averaging a massive amount of data. “Norma” represented such a truth. For Dickinson, the thousands of data points he had averaged revealed insight into a typical woman’s physique — someone normal.
      In addition to displaying the sculpture, the Cleveland Health Museum began selling miniature reproductions of Norma, promoting her as the “Ideal Girl,” launching a Norma craze. A notable physical anthropologist argued that Norma’s physique was “a kind of perfection of bodily form,” artists proclaimed her beauty an “excellent standard” and physical education instructors used her as a model for how young women should look, suggesting exercise based on a student’s deviation from the ideal. A preacher even gave a sermon on her presumably normal religious beliefs. By the time the craze had peaked, Norma was featured in Time magazine, in newspaper cartoons, and on an episode of a CBS documentary series, This American Look, where her dimensions were read aloud so the audience could find out if they, too, had a normal body.
      On Nov. 23, 1945, the Plain Dealer announced its winner, a slim brunette theatre cashier named Martha Skidmore. The newspaper reported that Skidmore liked to dance, swim, and bowl — in other words, that her tastes were as pleasingly normal as her figure, which was held up as the paragon of the female form.
      Before the competition, the judges assumed most entrants’ measurements would be pretty close to the average, and that the contest would come down to a question of millimetres. The reality turned out to be nothing of the sort. Less than 40 of the 3,864 contestants were average size on just five of the nine dimensions and none of the contestants — not even Martha Skidmore — came close on all nine dimensions. Just as Daniels’ study revealed there was no such thing as an average-size pilot, the Norma Look-Alike contest demonstrated that average-size women did not exist either.
      But while Daniels and the contest organizers ran up against the same revelation, they came to a markedly different conclusion about its meaning. Most doctors and scientists of the era did not interpret the contest results as evidence that Norma was a misguided ideal. Just the opposite: many concluded that American women, on the whole, were unhealthy and out of shape. One of those critics was the physician Bruno Gebhard, head of the Cleveland Health Museum, who lamented that postwar women were largely unfit to serve in the military, chiding them by insisting “the unfit are both bad producers and bad consumers.” His solution was a greater emphasis on physical fitness.
      Daniels’ interpretation was the exact opposite. “The tendency to think in terms of the ‘average man’ is a pitfall into which many persons blunder,” Daniels wrote in 1952. “It is virtually impossible to find an average airman not because of any unique traits in this group but because of the great variability of bodily dimensions which is characteristic of all men.”
      Rather than suggesting that people should strive harder to conform to an artificial ideal of normality, Daniels’ analysis led him to a counterintuitive conclusion that serves as the cornerstone of this book: any system designed around the average person is doomed to fail.
      Daniels published his findings in a 1952 Air Force Technical Note entitled The “Average Man”? In it, he contended that if the military wanted to improve the performance of its soldiers, including its pilots, it needed to change the design of any environments in which those soldiers were expected to perform. The recommended change was radical: the environments needed to fit the individual rather than the average.
      Amazingly — and to their credit — the air force embraced Daniels’ arguments. “The old air force designs were all based on finding pilots who were similar to the average pilot,” Daniels explained to me. “But once we showed them the average pilot was a useless concept, they were able to focus on fitting the cockpit to the individual pilot. That’s when things started getting better.”
      By discarding the average as their reference standard, the air force initiated a quantum leap in its design philosophy, centred on a new guiding principle: individual fit. Rather than fitting the individual to the system, the military began fitting the system to the individual. In short order, the air force demanded that all cockpits needed to fit pilots whose measurements fell within the 5-per-cent to 95-per-cent range on each dimension.
      When airplane manufacturers first heard this new mandate, they balked, insisting it would be too expensive and take years to solve the relevant engineering problems. But the military refused to budge, and then — to everyone’s surprise — aeronautical engineers rather quickly came up with solutions that were both cheap and easy to implement. They designed adjustable seats, technology now standard in all automobiles. They created adjustable foot pedals. They developed adjustable helmet straps and flight suits.
      Once these and other design solutions were put into place, pilot performance soared, and the U.S. air force became the most dominant air force on the planet. Soon, every branch of the American military published guides decreeing that equipment should fit a wide range of body sizes, instead of standardized around the average.
      Why was the military willing to make such a radical change so quickly? Because changing the system was not an intellectual exercise — it was a practical solution to an urgent problem. When pilots flying faster than the speed of sound were required to perform tough manoeuvres using a complex array of controls, they couldn’t afford to have a gauge just out of view or a switch barely out of reach. In a setting where split-second decisions meant the difference between life and death, pilots were forced to perform in an environment that was already stacked against them.
      Excerpted from The End of Average by L. Todd Rose © 2016. Published by HarperCollins Publishers Ltd. All rights reserved. Illustration used by permission of the Cleveland Museum of Natural History.

      Friday, September 14, 2018

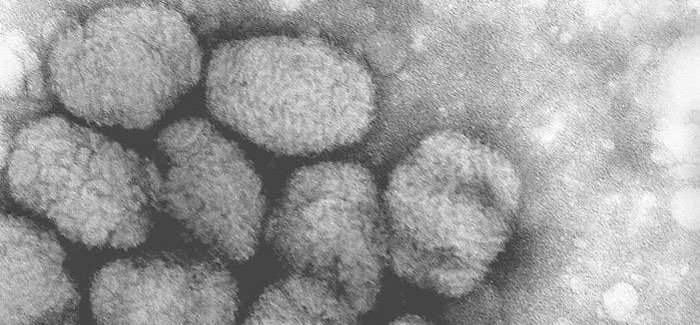
      History of medicine - the last case of smallpox